Evaluating the Efficacy of Stem Cells in Clinical Research for Diabetic Erectile Dysfunction
Explore recent clinical research evaluating stem cells for diabetic erectile dysfunction. Understand trial outcomes, vascular parameters, and clinical compliance.
Are you evaluating emerging therapeutic modalities for complex diabetic complications within a rigorous clinical framework? A randomized controlled clinical trial recently investigated the intracavernosal administration of stem cells for diabetic erectile dysfunction, demonstrating measurable improvements in vascular parameters and patient-reported outcomes over a six-month period. As the medical community advances these advanced cellular therapies, establishing a robust regulatory framework for stem cells in clinical research remains critical to ensuring patient safety, ethical compliance, and reproducible data integrity.
The Pathophysiology of Diabetic Complications and Clinical Unmet Needs
Diabetic erectile dysfunction (DMED) represents a highly prevalent and medically complex complication of diabetes mellitus. The underlying pathophysiology is multifactorial, primarily driven by sustained hyperglycemia that precipitates chronic vascular damage, peripheral neuropathy, and hormonal imbalances. Long-term poor glycemic control systematically compromises the endothelial integrity of penile blood vessels and disrupts normal neural signal transmission, thereby fundamentally impairing erectile capacity.
Epidemiological data indicates that up to 63.6% of male patients diagnosed with diabetes experience some degree of erectile dysfunction. Within the clinical landscape, DMED is widely recognized as one of the most intractable secondary conditions associated with diabetes. Because chronic hyperglycemia inflicts profound structural damage to the neurovascular networks of the corpora cavernosa, conventional first-line pharmacological treatments, such as oral phosphodiesterase type 5 (PDE5) inhibitors (e.g., sildenafil), frequently yield suboptimal or entirely ineffective results in this patient population.
Consequently, there is a pronounced clinical necessity to explore alternative therapeutic avenues. In recent years, regenerative medicine has introduced new translational paradigms. Investigational data from diverse medical disciplines suggests that cellular interventions may facilitate tissue repair and modulate localized hemodynamics. This broader application has catalyzed the hypothesis that targeted cellular therapies might address the underlying structural deficits of DMED, prompting investigators to transition these concepts into formalized clinical research.
Trial Design, Ethics Review, and Methodological Framework
To rigorously evaluate this therapeutic potential, the international medical journal Urology published the findings of a study on October 13, 2021, titled “Efficacy of intracavernosal injection of stem cells for the treatment of erectile dysfunction in diabetic patients: a randomized single-blind clinical trial.” The execution of such studies strictly requires comprehensive ethics review and adherence to global Good Clinical Practice (GCP) guidelines to ensure participant safety and reliable clinical translation.
Operating under these compliance standards, the investigators designed a randomized, single-blind clinical trial. The study enrolled 20 diabetic patients aged 50 to 70 years, all of whom presented with a documented clinical history of diabetes exceeding 10 years and had previously demonstrated resistance to standard ED treatments.
The participants were randomized into two equal cohorts: an intervention group (n=10) and a control group (n=10). For the intervention arm, autologous mesenchymal stem cells (MSCs) were carefully harvested from the patients’ oral mucosa, processed in accordance with strict quality control protocols, and subsequently administered via targeted intracavernosal injection (delivering a controlled volume of 50–60 × 10^6 cells). The control cohort received an equivalent volume injection of physiological saline.
Post-intervention monitoring relied on validated diagnostic tools. Participants were evaluated using the International Index of Erectile Function (IIEF5) questionnaire alongside objective color Doppler ultrasound imaging. Critical hemodynamic metrics, including peak systolic velocity (PSV), end-diastolic velocity (EDV), and the resistance index (RI), were systematically recorded at the three-month and six-month post-intervention marks.
Clinical Outcomes and Hemodynamic Parameter Evaluations
The collected data highlighted notable divergences between the two cohorts over the observation period. In the intervention group, the mean IIEF5 scores demonstrated a statistically significant upward trajectory (P = 0.01). The baseline score of 7.2 ± 2.1 progressed to 9.2 ± 3.4 at three months, and further increased to 10.6 ± 4.7 at the six-month follow-up. Based on the study’s specific evaluative parameters, two subjects in this group reported a resumption of morning erections at three and six months. Furthermore, by the three-month milestone, two patients indicated a restoration of functional capacity sufficient for intercourse during more than half of their attempts; by six months, this number expanded to four patients.
Conversely, the control group exhibited stable, unchanged metrics. Their IIEF5 scores remained static, recording 7.2 ± 2.1 at baseline, 7.2 ± 2.0 at three months, and 7.3 ± 2.1 at six months, indicating no spontaneous resolution of symptoms.
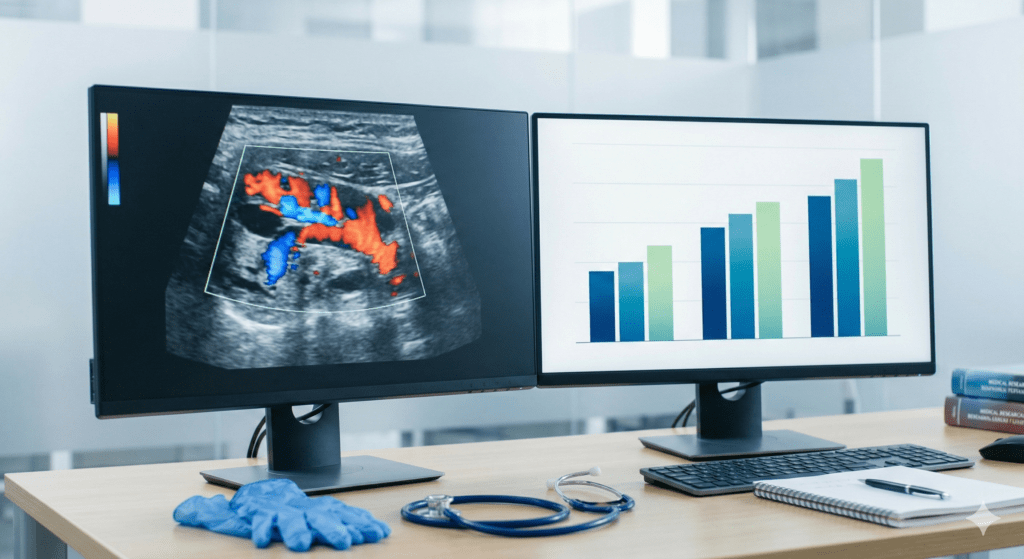
Objective hemodynamic imaging via penile vascular color Doppler ultrasound corroborated the questionnaire data. In the intervention arm, the baseline peak systolic velocity (PSV) of 8.26 ± 4.12 cm/s improved to 9.14 ± 2.56 cm/s at three months, reaching 10.22 ± 2.09 cm/s by six months. This sustained upward trend suggests an enhancement in penile arterial blood perfusion, a physiological mechanism critical for maintaining erectile function. The control group’s PSV metrics showed no significant deviation from their baseline of 8.21 ± 4.1 cm/s across the same intervals.
Additionally, the resistance index (RI) in the intervention group showed measurable normalization. Starting at a baseline of 0.77 ± 0.04, it shifted to 0.76 ± 0.09 at three months and improved to 0.81 ± 0.06 at six months, entering a range indicative of improved cavernous veno-occlusive function. The control group’s RI remained essentially static throughout the duration of the study.
Safety Profile and Regulatory Considerations
A paramount concern in the regulatory framework governing any cellular therapy is the careful documentation of adverse events. Throughout the duration of the treatment and the subsequent follow-up periods, researchers reported zero injection-related adverse reactions in both the intervention and control cohorts.
While the sample size of this initial trial is limited, the absence of acute adverse events provides preliminary support for the procedural safety of autologous mucosal MSC injections within this highly specific clinical context.

Advancing Cellular Medicine Through Compliant Research
The data derived from this randomized, single-blind trial suggests that the targeted application of stem cells for diabetic erectile dysfunction exhibits a favorable safety profile and measurable physiological efficacy over a six-month period. The documented improvements in validated patient questionnaires alongside objective hemodynamic markers (PSV and RI) highlight the translational potential of regenerative therapies for severe diabetic complications.
Moving forward, the validation of these findings necessitates larger, multi-center clinical trials. Continued scientific inquiry must be conducted within standardized regulatory frameworks, ensuring that future clinical translation is supported by rigorous long-term safety data, robust ethics review, and unwavering adherence to international compliance standards.